When Does My Baby Get the Whooping Cough Vaccine?

Your baby’s protection starts before birth, not at the two-month visit. Pregnancy Tdap covers the earliest gap. Then DTaP doses at two, four, and six months build your baby’s own protection.
SUMMARY
Routine infant DTaP doses are given at 2, 4, and 6 months. Boosters follow at 15–18 months and 4–6 years. CDC recommends Tdap during weeks 27–36 of every pregnancy. On-time vaccination lowers infection and severe-illness risk but cannot prevent every case. Ask your pediatrician about catch-up or local outbreak schedules.
Two vaccines, two jobs
DTaP and Tdap protect against diphtheria, tetanus, and pertussis. The letter sizes show different antigen amounts. DTaP is used for young children. Tdap is used for older children, adults, and pregnancy.
These vaccines cannot cause pertussis. They contain inactivated components rather than live pertussis bacteria. Their purpose is teaching the immune system before exposure.
Your baby’s routine DTaP timeline
| Dose | Routine age | Role |
|---|---|---|
| 1 | 2 months | Starts the primary series |
| 2 | 4 months | Builds protection |
| 3 | 6 months | Completes the primary infant series |
| 4 | 15–18 months | Boosts toddler protection |
| 5 | 4–6 years | Boosts protection before school |
This schedule appears in both CDC and Korean disease-control guidance. Combination vaccines may include DTaP with other routine vaccines. The visit may therefore have a different product label. Your record should still show the pertussis-containing dose.
Why the pregnancy dose matters
A newborn is too young for routine DTaP. Tdap during pregnancy helps bridge that gap. The pregnant parent makes antibodies and transfers them through the placenta before birth.
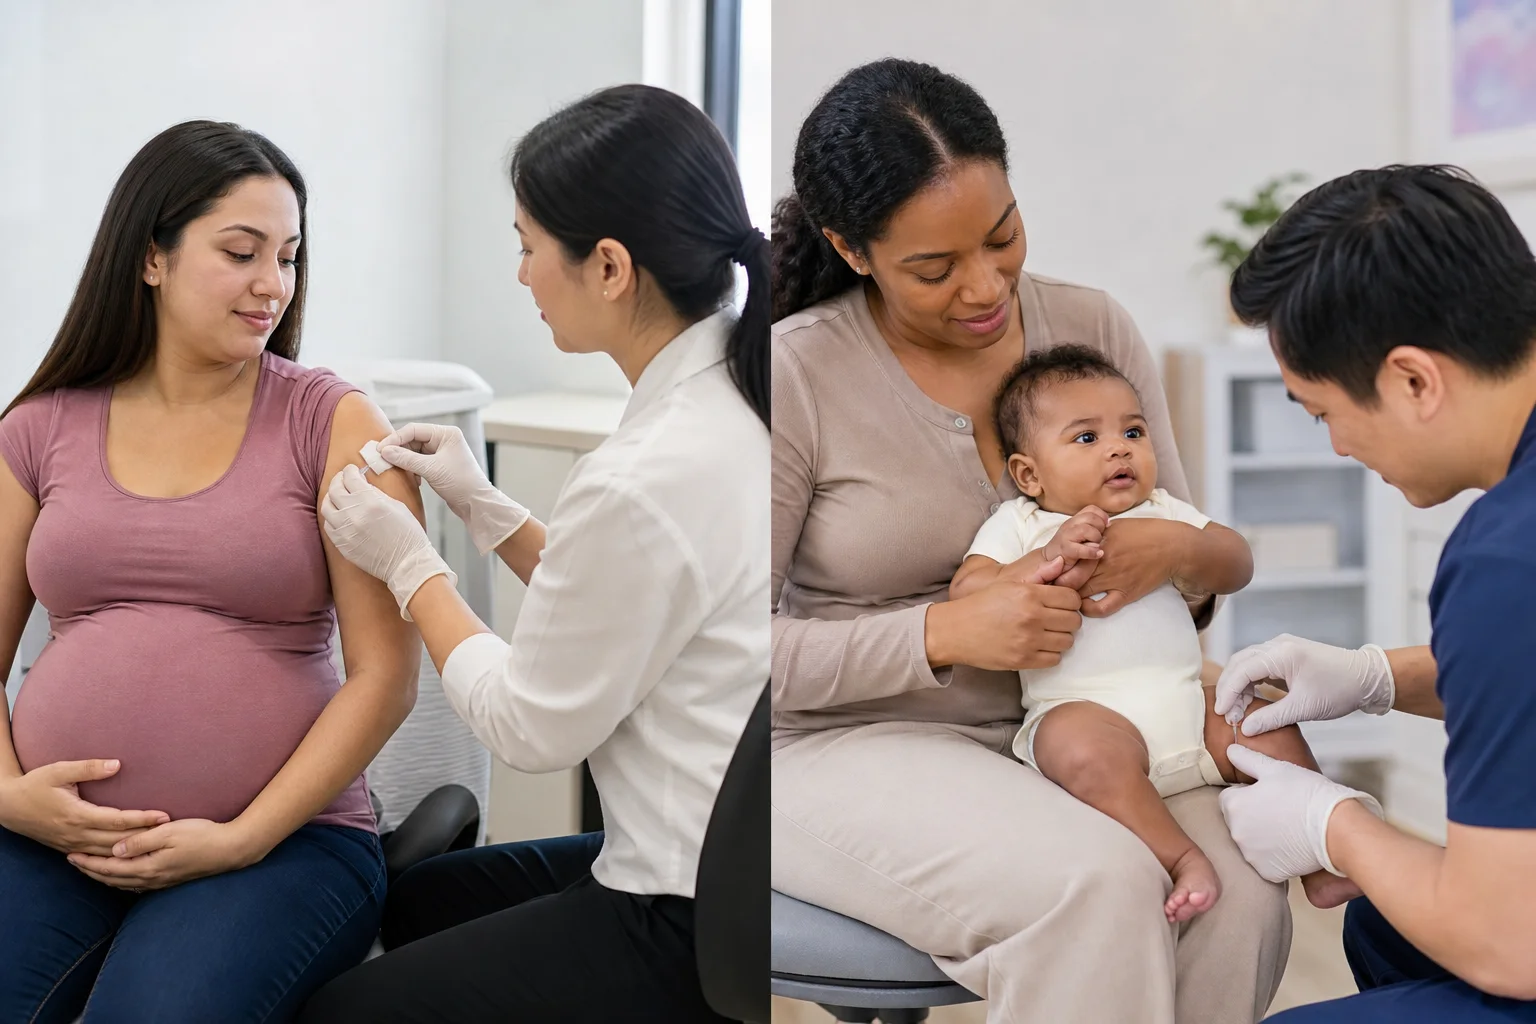
CDC recommends Tdap during weeks 27–36 of every pregnancy. It prefers the earlier part of that window. Antibodies need time to rise and reach the baby. A previous pregnancy dose does not replace the current one.
A CDC evaluation found a 78% lower pertussis risk in babies under two months. It also found protection against nine in ten serious infections needing hospital care. These numbers describe risk reduction, not a guarantee.
Why every dose still matters
Pregnancy antibodies fade during early infancy. They do not create lasting protection. Your baby must build their own immune response through DTaP doses.
One dose does not complete the series. Protection strengthens across the first three doses. Later boosters restore protection as immunity declines. Keep appointments even when pertussis activity seems low.
If a dose is late
Do not restart the entire series on your own. Catch-up schedules usually continue from previous valid doses. Exact spacing depends on age, product, and dose history. Ask your pediatrician or vaccination clinic to review the record.
During an outbreak, local authorities may recommend an accelerated start from six weeks. That is not the routine schedule. Follow an official local recommendation rather than moving dates yourself.
Vaccination after an exposure
Vaccination does not treat current pertussis. It also does not replace exposure assessment. CDC may recommend preventive antibiotics for high-risk infants or household contacts. That can apply even when vaccinations are current.
Call your pediatrician the same day after a confirmed household exposure. Share the exposure date and the patient’s cough-start date. Continue future DTaP doses unless your clinician gives different instructions.
What about parents and caregivers?
Adults should have at least one Tdap dose if they never received it. Later booster schedules depend on national guidance and individual history. Korean guidance recommends Td or Tdap every ten years after the adolescent dose.
Caregiver vaccination reduces one layer of risk. It cannot form a perfect protective circle. Coughing visitors should still stay away. Hand hygiene, ventilation, and rapid exposure reporting remain important.
When to call your pediatrician
Call if the record is missing or unclear. Also call after a late dose, serious previous reaction, or confirmed exposure. Ask before changing the schedule for travel or an outbreak.
Seek emergency help for breathing pauses, blue color, or severe breathing difficulty. Vaccination status should never delay emergency care.
Frequently asked questions
Can my baby start DTaP at birth?
No. Routine infant vaccination starts at two months. Some outbreak schedules may start at six weeks.
I received Tdap two years ago. Do I need it again while pregnant?
CDC recommends Tdap during every pregnancy, ideally during weeks 27–36.
Is my baby fully protected after three doses?
Risk is lower, but protection is not absolute. Later boosters remain important.
See the complete parent guide. If contact already happened, follow the exposure action plan.
Sources
This article is general information and is not medical advice. Ask your pediatrician about your baby’s exact vaccine schedule.