Intussusception symptoms: act now

Severe pain or screaming that keeps returning needs emergency assessment now; do not wait for blood in the stool.
For caregivers of babies and toddlers
SUMMARY
Looking well between painful episodes does not rule out intussusception and must not delay assessment.
Green, bile-stained vomit needs emergency care now because it can signal a blocked bowel.
If your child is hard to wake, is not responding normally or has severe trouble breathing, call your local emergency number immediately.
Recognize the pattern
Intussusception happens when one section of bowel slides into the next, which can block the bowel and reduce its blood supply.
It is most common in babies and toddlers, but it can happen at other ages, so age alone cannot rule it out.
A child may suddenly cry hard, pull their knees toward their chest and look pale during a painful spell.
The pain can come in waves, return more often and eventually become continuous; a quiet interval is not a reason to wait for the next spell.

Unexplained marked lethargy, meaning unusual sleepiness or very little energy, can be the only sign and needs urgent medical assessment even without obvious crying.
Vomiting, refusing feeds and a swollen belly are other warning signs, especially alongside repeated pain or unusual lethargy.

Jelly-like bloody stool
The jelly-like stool often called currant-jelly stool contains blood and mucus; it is a late sign and does not appear in every child.
Blood in the stool with severe bouts of pain needs immediate emergency assessment even if the stool does not look like jam.
Do not dismiss new, severe episodes as ordinary colic or wait for pain, a belly lump and bloody stool to appear together before seeking help.
Prompt treatment matters because an untreated blockage can damage the bowel and lead to a hole or serious infection.
While arranging emergency care
When intussusception is suspected and urgent assessment is being arranged, do not give food or drinks unless the treating team instructs you to.
Do not try an enema at home; the hospital procedure needs imaging and staff who can manage complications, including a tear in the bowel.
Tell the clinician when the episodes began, how they repeat, whether your child vomited or passed blood, and how alert they are between spells; do not delay leaving to make a record.

What happens at hospital
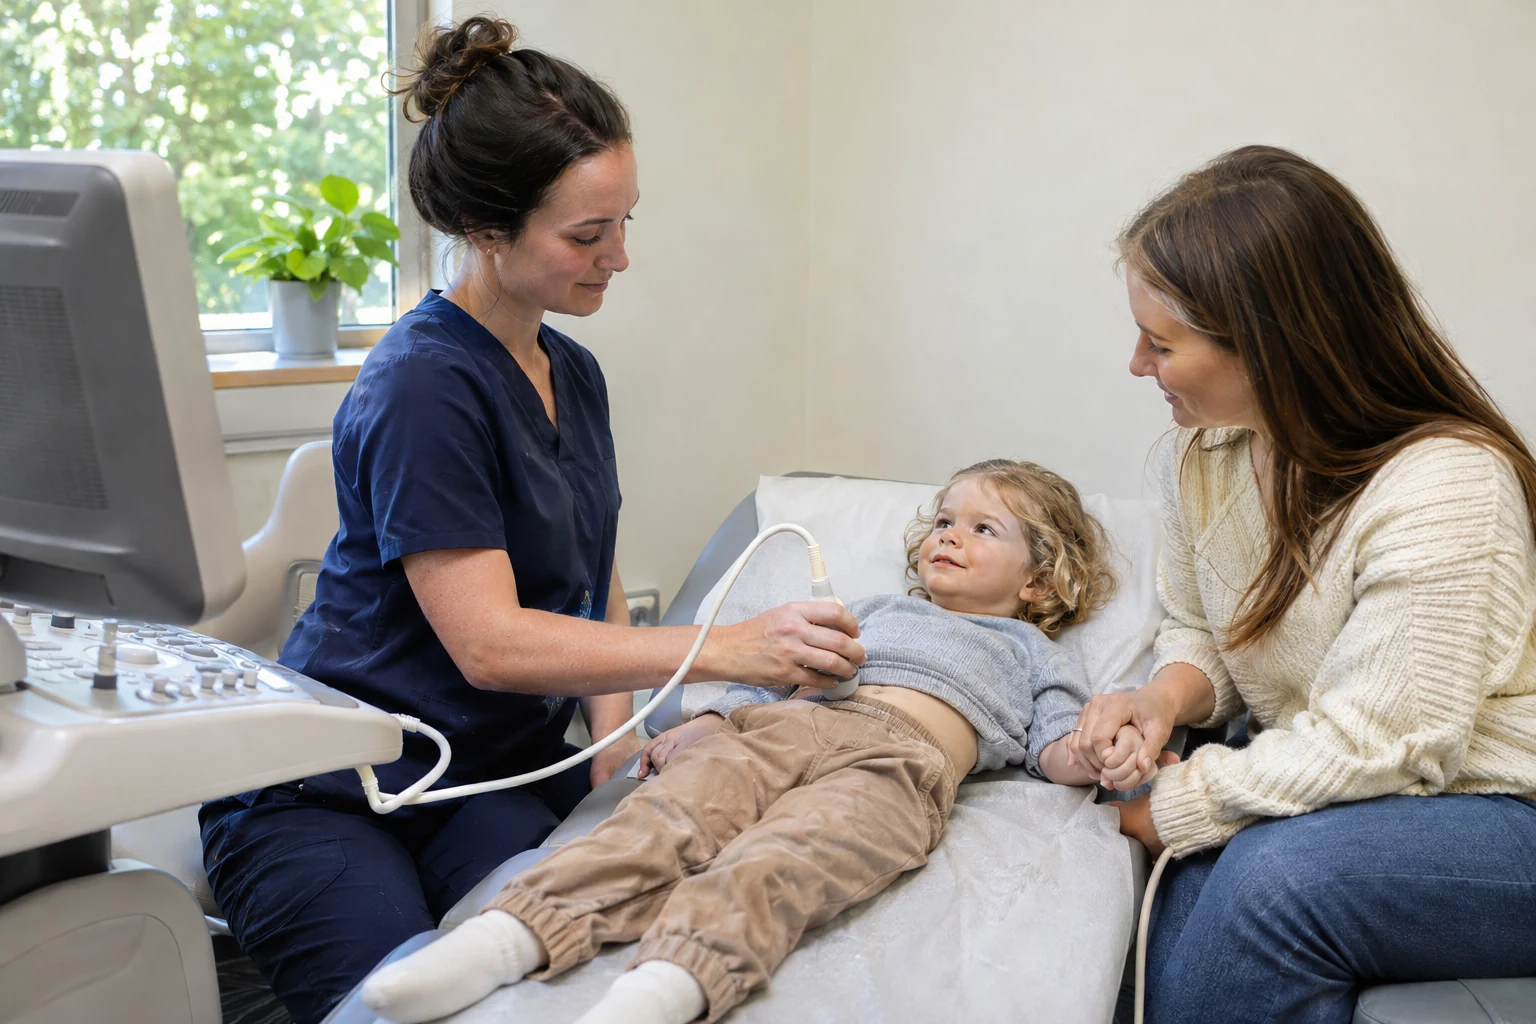
At hospital, an abdominal ultrasound is usually the first imaging test used to check for intussusception.
The team first checks your child’s condition and may give fluids through a vein and pain relief; a tube through the nose into the stomach may be needed to drain its contents.
An air or liquid enema, guided by imaging, can push the folded bowel back into place and may avoid an operation.
Surgery may be necessary if the enema does not work, your child is too unwell for it or the bowel is damaged; a badly damaged section may need removal.
After treatment
After treatment, the team watches your child and tells you when feeding can restart and when it is safe to go home.
Intussusception can come back after successful treatment, so return to emergency care immediately if the same symptoms return rather than waiting for bloody stool.

Questions caregivers ask
Could early diarrhoea mean it is only a stomach bug?
Diarrhoea can occur early in intussusception, so loose stools do not make repeated severe pain or unusual lethargy safe to watch at home.
Does a normal abdominal X-ray rule it out?
A normal abdominal X-ray does not rule out intussusception; persistent or returning symptoms still need reassessment.
Sources
- The Royal Children’s Hospital Melbourne — Clinical Practice Guidelines: Intussusception
- Great Ormond Street Hospital for Children NHS Foundation Trust — Intussusception
- Cambridge University Hospitals NHS Foundation Trust — Intussusception – in children
- Seattle Children’s — Intussusception
- NHS — Diarrhoea and vomiting