Baby Length and Head Measurement

Infants younger than 2 years are measured lying down for recumbent length, not standing height. Head circumference uses a non-stretch tape around the largest circumference. Position and technique matter enough that an improvised ruler or loose tape can create a misleading percentile.
SUMMARY
A trained measurer may need a second adult to hold the head and align the legs safely on a length board. Head circumference should pass above the eyebrows and around the most prominent back of the head without compressing skin. Repeat an unexpected result, record exact age and sex, and compare a series on the appropriate standard. Ask the pediatrician about rapid crossing, slowing, asymmetry, unusual head shape, or developmental concern.
Build a series, not a verdict
Start with recumbent length board. A growth chart is a screening and monitoring tool, not a diagnosis or report card. One point describes size at one moment; a series of accurate measurements shows direction and pace. Record exact dates and age, and include gestational age and birth size. Do not compare a baby with siblings, social media, or a generic adult calculator. Ask what changed across visits and whether an unexpected point was repeated before interpreting the line.
Use the correct growth standard
Confirm largest head circumference. Select the age- and sex-specific standard recommended in your country. In the United States, CDC and AAP recommend WHO Child Growth Standards from birth to 2 years for both breastfed and formula-fed infants. These include weight-for-age, recumbent length-for-age, weight-for-length, and head circumference-for-age. BMI-for-age is not recommended for routine interpretation under age 2. Switching charts or entering age incorrectly can create an apparent change that is not biological.
Measure weight accurately
Use a maintained, calibrated infant scale on a stable surface with trained technique. Zero the scale, use minimal consistent clothing, account for diaper differences, and keep an adult within reach without pressing on the scale. Movement, rounding, recent feeds, stool, urine, clothing, and different devices can change a small reading. Repeat an implausible result. Home measurements can support a clinician-directed plan, but frequent unsupervised weighing may add noise and anxiety rather than useful evidence.
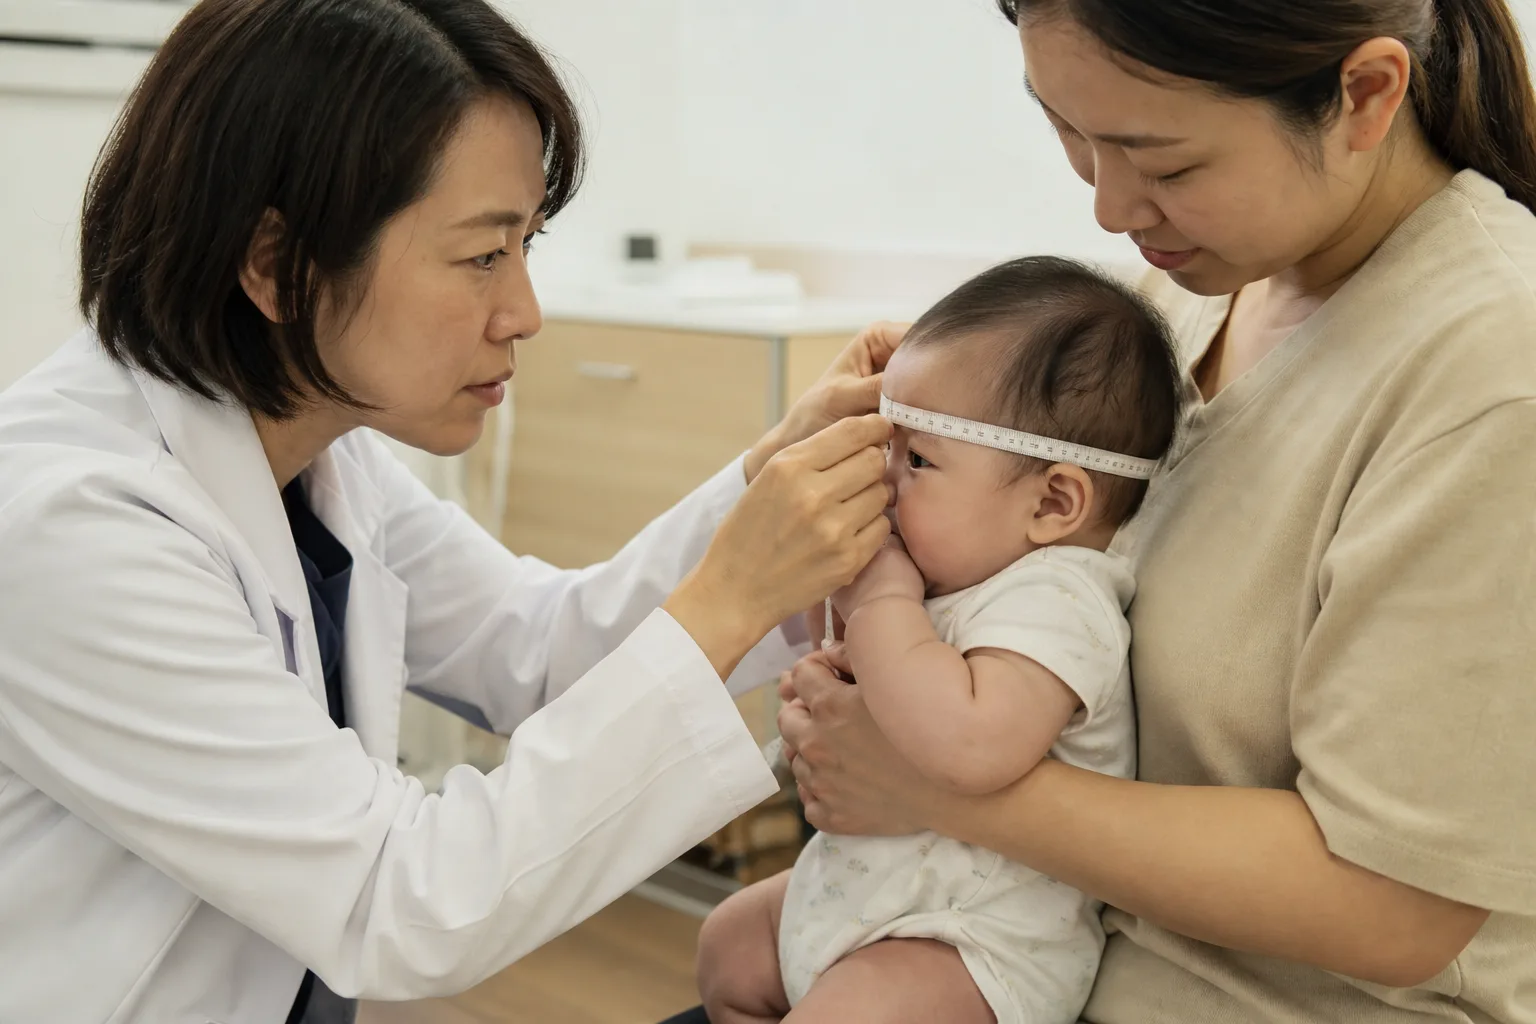
Measure length and head circumference
Infants are measured lying down on a proper length board, usually with two trained adults aligning the head and legs safely. Head circumference uses a non-stretch tape over the eyebrows and around the most prominent back of the head without compressing tissue. Repeat unexpected measurements and plot exact age and sex. Length and head circumference add context that weight alone misses. Ask about rapid crossing, slowing, asymmetry, unusual head shape, or developmental concerns rather than diagnosing from a home tape.
Interpret the whole baby
Review repeat and exact age. Consider breast and formula feeding, formula preparation, complementary foods, wet diapers, stool, vomiting, illness, medications, feeding skill, development, activity, gestational age, birth size, chronic conditions, and parental stature. A stable smaller baby feeding and developing well differs from a sudden downward trend with poor intake. Breastfed and formula-fed infants can have different growth patterns, but the appropriate standard and clinical context apply to both.
Avoid unsafe attempts to move a percentile
Do not concentrate formula, dilute it, add cereal to a bottle, force-feed, wake excessively, restrict milk, start supplements, or remove food groups solely to change a percentile without clinical guidance. These actions can cause electrolyte, nutrition, aspiration, allergy, or feeding problems. Keep usual safe feeding while arranging review unless a clinician gives a specific plan. A feeding observation, formula-mixing check, diet history, laboratory evaluation, or specialist assessment may be more useful than simply increasing calories.
Know when to contact the pediatrician
Use serial clinical interpretation. Contact the pediatrician for a confirmed slowing, plateau, loss, or disproportionate pattern; feeding refusal; exhausting or very long feeds; repeated cough, choking, or sweat with feeds; vomiting or diarrhea; fewer wet diapers; persistent pain or fever; developmental slowing; or strong caregiver concern. Bring the measurement method and dates, feeding and diaper record, symptoms, birth history, medicines, and previous chart. Do not wait weeks for another home point when intake or health has changed.
Put emergency signs before measurement
Breathing trouble, blue or gray color, collapse, seizure, inability to wake, severe lethargy, signs of severe dehydration, green or bloody vomit, or an acutely very ill appearance needs emergency help. Stop trying to weigh, photograph, or plot the baby. Follow local emergency guidance. After stabilization, the growth trend can help the clinical history, but an emergency is never resolved by a normal percentile or a single recent weight.
Frequently asked questions
Can one wet diaper rule out dehydration?
No. Use the full-day trend, feeding, and whole-body signs.
Should I give water to fix a low count?
Not to an infant under six months unless a clinician specifically directs it. Ask your pediatrician.
Can I wait until the log is complete?
No. Emergency signs or a clear contact threshold take priority over documentation.
Sources
This article provides general information and is not medical advice. Ask your pediatrician about reduced urine, feeding concerns, or guidance tailored to your baby.